


What Makes Feedback Hard to Receive
A resident hears “your suturing needs work” at the end of a twelve-hour shift. By the word needs, she has already stopped listening.
That reaction is not a character flaw. Feedback only changes behavior once it survives what researcher Christopher Watling calls a credibility judgment (Watling, 2014). That is a rapid, often unconscious test of whether the information deserves attention at all. Feedback competes with other signals, like a patient’s reaction or a supervisor’s expression, for a trainee’s attention. It wins that competition only if the listener decides it is worth trusting.
Medicine makes this harder than it needs to be. Watling’s research compared medicine with music and teacher training. Both of those cultures build direct observation into how they teach, which gives their feedback built-in credibility. Clinical training often skips that step, so trainees are left judging feedback’s credibility with less evidence to go on. The techniques below close that gap from the receiving end. The culture around trainees will not close it on its own.
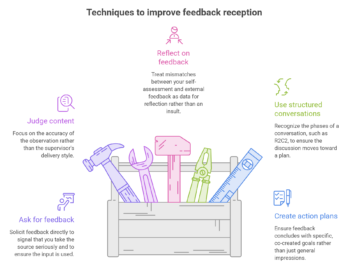
Technique 1: Ask for It Instead of Waiting for It
Feedback you asked for lands differently than feedback you receive unannounced. Trainees trust it more, and they act on it more often, because asking is itself a signal that they take the source seriously.
Natesan and colleagues (2023) identified four factors that shape whether a trainee seeks out feedback at all. These are feedback quality, the trainee’s emotional state, the relationship with the giver, and workplace culture. Only the first two sit within a trainee’s daily control, which is exactly where to focus.
In practice, that means asking a specific question rather than a general one. “How was my presentation today?” invites a vague answer. “Did my differential for chest pain make sense, and what would you add?” invites a real one. The second version signals that the input will actually be used. That is what makes a supervisor willing to give feedback in detail.
A structured moment, like an OSCE debrief, already builds this solicitation in. Outside of one, a trainee has to create it themselves, and asking directly is the fastest way to do that.
Technique 2: Judge the Content, Not Just the Delivery
A blunt delivery does not make feedback wrong. A warm one does not make it right either.
Watling’s research describes credibility judgment as the filter every piece of feedback passes through before it can influence a learner (Watling, 2014). The risk is that this filter runs on the wrong signal. A supervisor who delivers a correction awkwardly is not necessarily giving worse information. Too fast, too flat, without softening, the content can still be right. Trainees who let tone override content make two mistakes. They discard accurate feedback because the messenger was clumsy, or accept weak feedback because the messenger was likeable.
The fix is a habit, not a personality trait. Before reacting to how something was said, ask what was actually said. Would this observation hold up if a different supervisor had made it? If the answer is yes, the delivery is a separate problem. The content still deserves a response.
Technique 3: Reflect on It Instead of Rating Yourself Against It
Trying to rate your own performance accurately is not a reliable skill. Decades of self-assessment research say so plainly.
Eva and Regehr (2005) reviewed that research and reached a stark conclusion. People cannot judge their own ability in any stable way, regardless of experience. Their recommendation was direct. Stop trying to become a more accurate self-rater. Instead, seek out external feedback and take it seriously once it arrives. As the authors put it, the goal is “to reflect rather than ruminate.”
The gap this closes is measurable in emergency medicine training specifically. Residents consistently rate themselves higher on ACGME milestones than their attendings do (Natesan et al., 2023). That mismatch is not a sign of arrogance. It is exactly what the self-assessment literature predicts. Relying on your own judgment instead of external input produces this kind of mismatch.
The practical shift is small. When feedback contradicts your own sense of how you did, treat the mismatch as data, not an insult. Reflection means asking what the gap reveals. Rumination means replaying the moment without asking anything at all.
Technique 4: What a Structured Conversation Adds That an Unstructured One Doesn’t
Without a structure to follow, a feedback conversation tends to stall at the emotional reaction and never reach a plan.
Sargeant and colleagues (2015) developed a four-phase model for exactly this problem, tested with physicians receiving real performance reports. The phases are relationship, reactions, content, and coaching, known together as R2C2. A conversation opens by building trust. It moves through the recipient’s initial reaction to the data. Then it works through what the data means, before turning to a concrete plan for change.
Physicians who went through this process reported that it helped. One facilitator described the structure as something that put people’s minds at ease, since everyone knew what came next instead of the discussion feeling scattered.
A trainee cannot always control who runs a feedback conversation, but they can recognize which phase they are in. If a supervisor jumps straight to solutions before asking how the trainee reacted, that is a sign. It is fair to ask for a moment to respond first. The structured models used across healthcare education, including Ask-Tell-Ask, all exist to prevent exactly that shortcut.
Technique 5: Leave With an Action Plan, Not Just an Impression
Feedback that ends without a specific next step rarely changes what happens the next time.
Best-practice guidance from emergency medicine residency directors recommends building co-created goals and action plans directly into feedback conversations (Natesan et al., 2023). A trainee should not have to do that work alone afterward. The distinction matters. An impression like “work on your suturing” gives a trainee a feeling, not a task. A plan like “suture the next three closures under direct supervision and ask about needle angle” is different. It gives them something to actually do.
This is also where the coaching phase of a structured conversation earns its place. Sargeant and colleagues (2015) found that physicians who reached this phase left with a plan they believed was achievable. It felt like their own plan, not one someone else had assigned.
Before a feedback conversation ends, a trainee can ask one direct question. What should be different next time this situation comes up? If the answer is vague, the conversation is not finished yet.
Why Recorded Assessments Make Reflection Easier
A resident remembers the tone of a correction more clearly than its content, especially an hour after the shift ends.
Recorded assessment changes what a trainee has to work with afterward. An OSCE station or a workplace encounter captured on video is still there the next day. A trainee can review it at whatever pace actually supports reflection, not rumination. They can watch the moment a supervisor flagged. They can compare it against the verbal feedback given at the time. Then they can decide whether the content holds up, separate from how it felt to hear it live.
That same recording gives the coaching phase something concrete to point to. Instead of building an action plan on a half-remembered impression, both sides can cue up the actual footage. Then they can agree on exactly what should look different next time. Our guide to video in competency-based medical education covers how programs build this into routine assessment, beyond high-stakes exams.
Frequently Asked Questions
Why does feedback feel harder to receive than to give?
Feedback only changes behavior once it survives a listener’s credibility judgment, a rapid test of whether the information is worth trusting (Watling, 2014). Medicine’s training culture rarely builds in the direct observation that other fields, like music or teacher training, use to make feedback credible from the start. That leaves trainees doing more of that credibility-checking work themselves, in the moment, which is what makes receiving feedback feel harder than giving it.
How do I ask for feedback without seeming unsure of myself?
Asking a specific question, rather than a general one, signals confidence rather than insecurity. “What would you have added to my differential for the chest pain patient?” shows a supervisor exactly what you want to improve, which is what makes them willing to give a detailed answer. A vague request like “how did I do?” is what actually reads as unsure, because it gives the supervisor nothing to work with.
What’s the difference between reflecting on feedback and dwelling on it?
Reflection asks what a piece of feedback reveals and treats a mismatch between your self-view and the feedback as useful data (Eva & Regehr, 2005). Rumination just replays the moment, usually focused on how it felt, without asking anything new. The practical test is whether you come away with something to do differently, not just a feeling about what was said.