

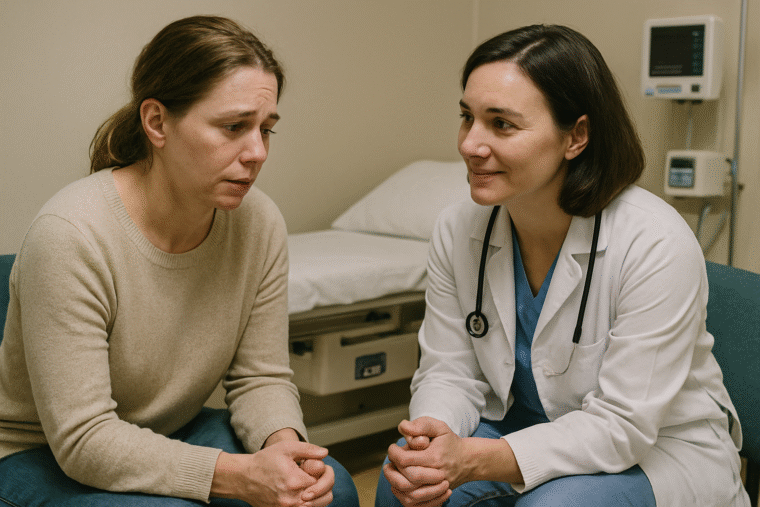
Patient anxiety is a common challenge in healthcare settings. Whether someone is awaiting test results, facing a medical procedure, or navigating a new diagnosis, anxiety can cloud communication, delay care, and lower overall satisfaction. Even routine interactions can feel overwhelming in high-stress moments like emergency room visits, invasive treatments, or critical care discussions.
Anxious patients show it in different ways. Some become restless or tearful. Others go quiet, breathe shallowly, or answer in as few words as possible. Spotting and managing these reactions quickly is a clinical skill, not just good bedside manner. Patients who feel heard and reassured are more likely to follow their care plan, understand instructions, and come back for follow-ups.
Research backs this up. Structured protocols like the SPIKES model, built for delivering serious news, treat empathy and shared understanding as core components of effective communication. Roberts’ Crisis Intervention Handbook makes a similar point: timely emotional support stabilizes patients and improves outcomes, especially under acute stress.
Even tense situations become manageable with the right approach. The sections below cover techniques that reduce anxiety and build trust, the kind of tools every care provider should have on hand.
Understanding Patient Anxiety
Not all anxiety looks the same, and telling clinical anxiety apart from situational anxiety changes how you support the patient. Clinical anxiety is persistent, excessive worry that interferes with daily life, usually diagnosed as GAD (Generalized Anxiety Disorder) or panic disorder and often needing long-term management or medication. Situational anxiety is short-term, triggered by a specific circumstance such as a hospital visit, a procedure, or bad news.
Telling the two apart matters because it changes what kind of support actually helps. Situational anxiety often shows up physically: rapid breathing, restlessness, irritability, dry mouth, sweating, shaking, or freezing up. Patients may avoid eye contact, seem overwhelmed, or ask the same question more than once. An elevated heart rate or nausea is common too, and clinicians often notice indecisiveness or trouble putting concerns into words.
Anxiety affects communication in a few specific ways. It shortens attention span, so patients absorb fewer details and instructions. Emotional arousal also pulls the brain away from logical processing and toward survival responses, which can produce confusion, poor decisions, or mistrust of clinical guidance. In high-stress moments, even a routine interaction can feel threatening, which lowers cooperation and raises emotional reactivity.
The Psychology of Reassurance
Reassurance is a psychological skill, not a script. Effective communication depends less on the exact words used and more on how they are delivered, how much emotional support the patient feels, and whether their sense of control stays intact. Two well-established models in medical communication, the SPIKES protocol and Roberts’ Crisis Intervention model, offer a useful framework for both.
Communication Models in Action
SPIKES Model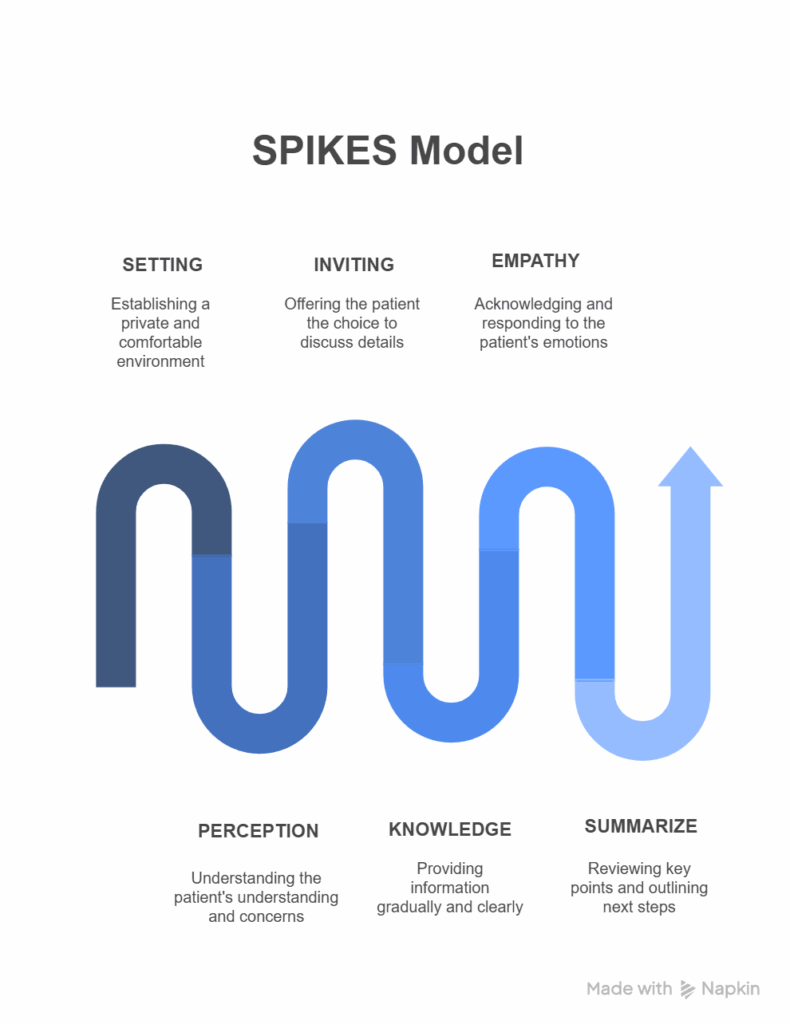
SPIKES was originally built to guide difficult conversations in oncology. It breaks a patient interaction into six steps: Setting up the conversation, checking the patient’s Perception, getting Invitation to share information, giving Knowledge, addressing Emotions with empathy, and closing with a Strategy and summary. Outside cancer care, the same structure still works: empathy paired with a clear framework calms patients and keeps clinicians on track.
- Setting – Create privacy and eliminate distractions. Sit down, maintain a calm tone, and ensure the patient feels physically and emotionally safe.
- Perception – Ask what the patient understands about the situation so far. Let them explain in their own words.
- Invitation – Gauge how much detail they want. Some anxious patients may prefer simple, high-level information at first.
- Knowledge – Explain what’s happening in clear, non-technical language. Use analogies if needed.
- Empathy – Acknowledge emotions directly. Phrases like “It makes sense that you’re feeling this way” validate their experience.
- Strategy & Summary – Outline what’s next and ensure they know they’re not facing it alone. Reconfirm availability and next steps.
Used this way, SPIKES stops being just a disclosure framework and becomes a tool for anchoring patients in clarity and trust. It’s a common recommendation in clinical training for high-stress environments, including emergency and critical care. For a deeper look at the model, see this blog.
Roberts’ 7-Stage Crisis Intervention Model
Dr. Albert Roberts developed this model to break crisis de-escalation into actionable steps. Its seven stages center on building rapport, validating emotions, exploring coping skills, and forming an action plan together with the patient. It was built for acute psychiatric crises, but the same steps work well for managing anxiety in medical or therapeutic settings.
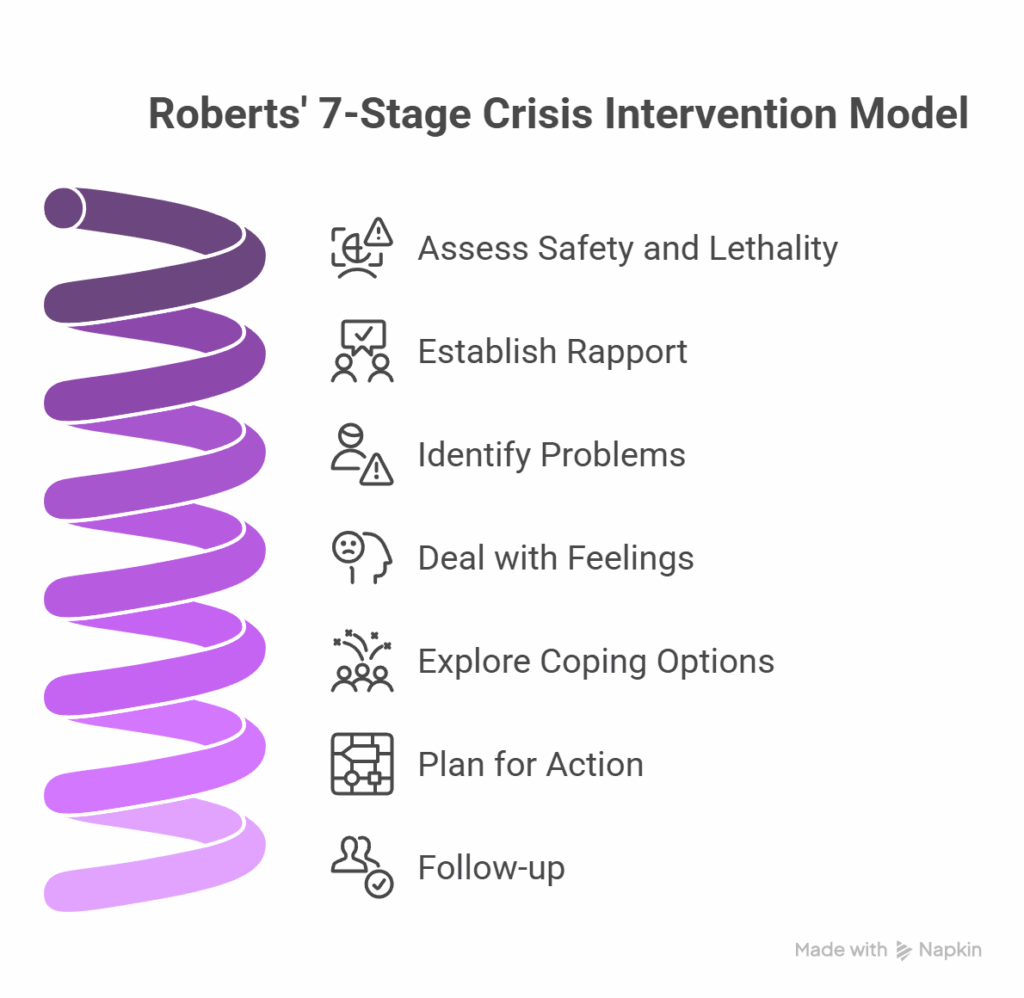
- Assess safety and lethality – Quickly identify if the patient is at risk of harm to self or others. If not, move to emotional assessment.
- Establish rapport – Use open body language and reflective listening. Avoid interrupting. Rapport builds faster when patients don’t feel judged.
- Identify problems – Ask what triggered their anxiety today. Clarify if it’s related to pain, diagnosis, isolation, or other factors.
- Deal with feelings – Let the patient express emotions freely. Normalize their experience with gentle prompts like, “A lot of people feel this way here.”
- Explore coping options – Collaborate on what’s worked for them in the past and suggest short, immediate calming techniques like paced breathing.
- Plan for action – Propose a clear plan: it could be speaking with a nurse regularly, getting reassurance before each procedure, or having a loved one present.
- Follow-up – Recheck later that day or during the next visit. Consistency strengthens trust.
Empathy helps patients feel understood, which lowers perceived threat. Treating patients as active participants, offering clear options and space to speak, helps them regain a sense of control. Emotional safety grows when patients aren’t rushed, judged, or silenced.
Why communication changes the patient’s emotional state
In healthcare settings, anxiety is not only shaped by symptoms or diagnosis. It is also strongly influenced by communication. Patients often become more distressed when they do not understand what is happening, how long they will wait, or what happens next.
Recent NHS England qualitative analysis of urgent and emergency care experiences found that uncertainty, poor expectation management, and inconsistent communication significantly increased stress during care experiences. Patients repeatedly linked reassurance to simple but consistent behaviors such as being listened to, receiving updates, and having procedures clearly explained.
The report identified “trust and confidence” as a central factor in patient experience, particularly during periods of waiting and uncertainty. Patients described feeling calmer when staff communicated clearly, explained delays honestly, and acknowledged emotional concerns rather than focusing only on clinical tasks.
Several patient accounts specifically highlighted the calming effect of supportive communication:
“The A&E staff were so good at informing me, especially as was very nervous – Broken wrist, they were all very good and helped me stay calm and explained everything.”
Other responses showed the opposite pattern. Anxiety often escalated when patients felt ignored, dismissed, or left without updates for long periods. NHS England’s analysis noted that lack of communication around waiting times created additional stress and frustration, especially in already vulnerable patients.
This reflects an important principle in patient-centered communication: reassurance does not come primarily from saying “don’t worry.” It comes from reducing uncertainty. Clear explanations, active listening, emotional acknowledgment, and predictable next steps help patients regain a sense of orientation and safety during care interactions.
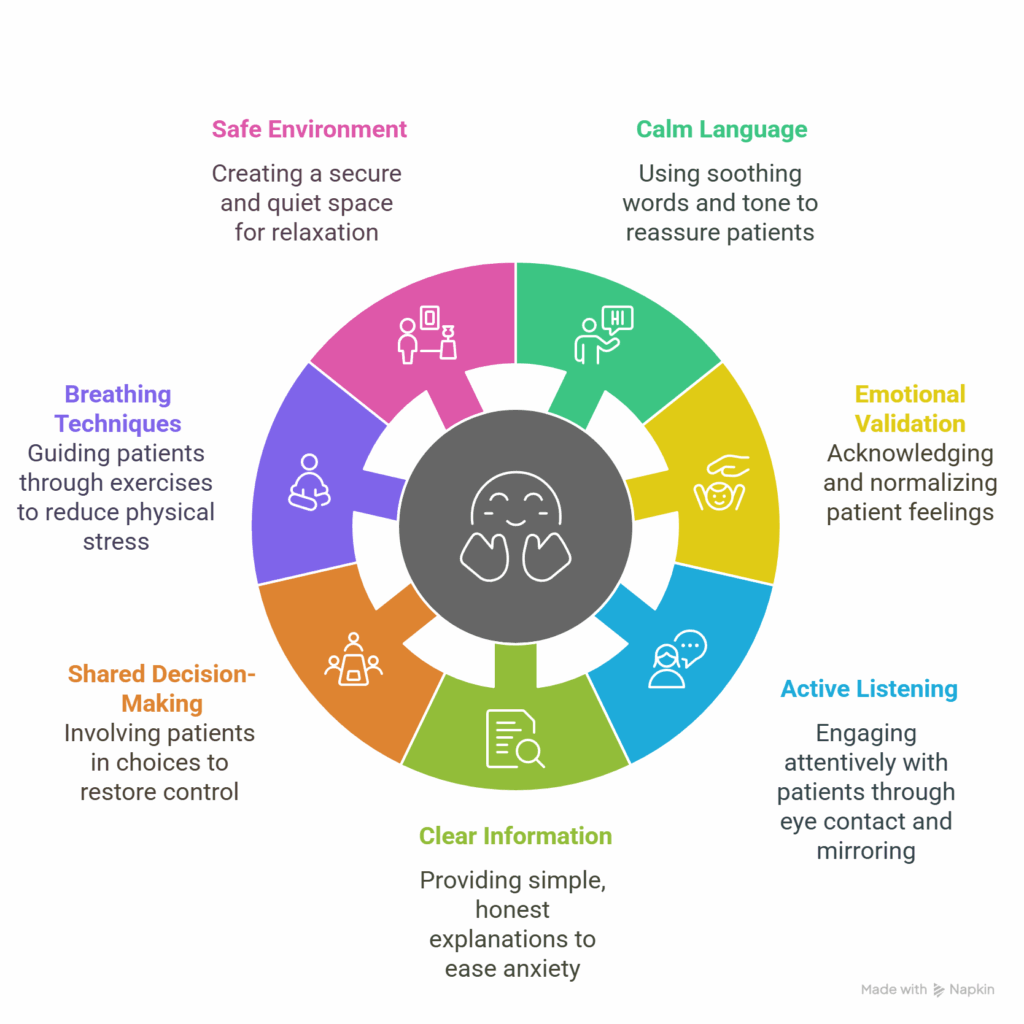
7 Evidence-Based Techniques to Calm and Reassure Patients
1. Use Calm, Reassuring Language
Tone sets the stage. Speak slowly and clearly, using simple words, and avoid medical jargon unless you explain it. Phrases like “You’re safe here” or “We’ll go one step at a time” reduce distress quickly. Even a warm, present greeting helps anchor the patient before you say anything clinical. Calm language shapes how safe a patient feels, not just what they understand.
2. Acknowledge and Normalize Their Emotions
Let patients know their anxiety is valid. Avoid dismissing or minimizing their fears. Say things like “It’s completely okay to feel nervous about this” to show you’re listening. Recognizing anxiety without trying to ‘fix it’ immediately builds rapport. As noted by Hopkins Medicine, emotional validation often lowers physical signs of stress.
3. Practice Active Listening and Eye Contact
Patients are quick to pick up on where your focus lies. Put away distractions, make steady eye contact, and mirror their emotions with attentive body language. Reflecting or paraphrasing what they say shows you’re listening, not just hearing. These nonverbal cues build trust rapidly. This blog on nonverbal communication in healthcare highlights how eye contact and posture directly impact patient comfort and reduce anxiety during medical interactions.
4. Provide Clear, Honest Information
Clarity eases anxiety. When patients don’t understand what’s happening, their stress increases. Break information into small, manageable chunks and avoid overloading them. Use simple language, and follow up by asking if anything needs repeating. Visual aids, like diagrams or written instructions, can reinforce verbal communication. When discussing outcomes, stay honest but compassionate. Phrases like “We’ll handle this together” can balance honesty with emotional reassurance.
5. Involve the Patient in Decision-Making
Shared decision-making helps restore a sense of control. Offer choices when possible, whether it’s picking a time for a procedure or deciding on a treatment path. Studies have shown that the act of collaboration reduces emotional tension and increases satisfaction with care.
6. Offer Breathing or Grounding Techniques
Guided breathing and grounding can quickly reduce physiological symptoms of anxiety like rapid heartbeat, dizziness, or chest tightness. A simple breathing exercise involves inhaling slowly through the nose for four seconds, holding for four, and exhaling through the mouth for six. This activates the parasympathetic nervous system and helps calm the body.
Grounding techniques work by shifting focus away from internal anxiety and toward the external environment. One popular method is the 5-4-3-2-1 technique: patients are asked to name five things they can see, four they can touch, three they can hear, two they can smell, and one they can taste. This engages the senses and reduces spiraling thoughts.
7. Create a Safe, Quiet Environment
Anxiety often escalates in chaotic or overstimulating spaces. Make the setting feel secure by reducing noise, dimming harsh lighting when possible, and maintaining physical boundaries like closed doors or privacy curtains. A stable, sensory-controlled space plays a real role in easing patient anxiety, especially somewhere unfamiliar.
Mistakes to Avoid When Reassuring Anxious Patients
Good intentions can backfire if they’re not handled with care. One common mistake is overpromising. Saying “everything will be fine” sounds comforting, but it undermines trust once outcomes turn out uncertain. Offer realistic support instead, focused on what can be done right now.
Ignoring or minimizing a patient’s concerns is another frequent error. Phrases like “don’t worry” or “you’re overthinking it” feel dismissive and tend to increase distress. Acknowledging the emotion instead shows empathy and builds rapport.
Rushing the conversation or leaning on medical jargon is just as counterproductive. It creates confusion, raises anxiety, and leaves patients feeling unheard. Slowing down and explaining things in everyday language fixes most of that on its own.
These missteps are easy to make under pressure, but staying mindful of them cuts the risk.
Conclusion
There’s no perfect script for calming an anxious patient. What matters is presence, clarity, and connection. Anxiety clouds decision-making, interrupts care, and erodes trust, but simple, consistent habits, like listening actively, explaining clearly, and validating emotions, help patients feel safe, understood, and involved.
The SPIKES model and Roberts’ Crisis Intervention framework aren’t reserved for extreme situations. They’re practical blueprints for everyday communication, especially under pressure. Respond with empathy and structure, and patients engage more, follow through on care more consistently, and come back for follow-ups.
Healthcare is full of uncertainty, but reassurance is one thing you can control. Sometimes the calm you offer is the difference between fear and trust.
For more on emotionally intelligent communication, see our post on patient-centered care.
Frequently asked questions
How do you calm an anxious patient before a procedure?
Start by acknowledging the anxiety directly rather than minimising it. Phrases like “it makes sense that you are feeling nervous” signal that you are listening. From there, a brief explanation of what will happen and what the patient will feel reduces anticipatory anxiety more reliably than general reassurance. Non-verbal cues matter equally here — see our guide on mirroring body language in clinical consultations for practical techniques you can use from the first moment of contact.
What causes anxiety in patients during clinical consultations?
Patient anxiety usually comes from uncertainty, loss of control, or previous negative experiences with healthcare. The clinical environment itself often contributes, including unfamiliar equipment, formal terminology, and time pressure that makes patients feel like a burden. Clinicians who slow their pace and use plain language consistently report more cooperative and less distressed patients.
Does patient anxiety affect clinical outcomes?
Yes, and the evidence is well established. Anxious patients are less likely to recall post-consultation instructions, less likely to adhere to treatment plans, and more likely to experience heightened pain perception during procedures. Addressing anxiety is therefore not only a communication skill but a clinical one with direct downstream effects on care quality.
What is the difference between reassurance and empathy in patient communication?
Reassurance tells a patient that everything will be fine. Empathy acknowledges what they are feeling without making a prediction about the outcome. Research consistently shows that empathy is more effective than reassurance in reducing patient distress, partly because patients often sense when reassurance is not grounded in their specific situation. When a consultation involves visible patient distress, the techniques covered in de-escalation in healthcare complement the empathy-first approach well.
How does non-verbal communication help calm an anxious patient?
Non-verbal cues often carry more weight than spoken words in high-anxiety situations. Maintaining eye contact, adopting an open and relaxed posture, and matching the patient’s pace of speech all signal safety and attentiveness. Sitting down rather than standing, when possible, has been shown to increase patient perceptions of time spent with them, even when the consultation length is identical.
How do you identify when a patient is anxious but not saying so?
Patients frequently mask anxiety with brevity, deflection, or overcooperation. The signs are usually physical: shallow breathing, reduced eye contact, clipped sentences, or a slight increase in vocal pitch. Developing the ability to read these signals accurately is a trainable skill. Our post on identifying emotional cues during a consultation covers the specific behaviours to watch for and how to respond to each one.